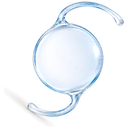
The artificial lens placed during cataract surgery or refractive lens exchange, called an intraocular lens or IOL, comes in several designs. This page compares them in plain terms.
What does an intraocular lens look like?
Turn the lens through 360° and explore its details. Choose an optic design and add toric markings.
The standard lens. It focuses at one distance, most often set for distance, so that driving, television and walking about are clear without glasses and reading glasses are worn for close work. Some people choose the reverse. Optically the simplest, with the fewest night-time effects, and suitable for almost every eye, including eyes with retinal disease.
02
Extended depth of focus
A lens that stretches a single focus into a range, typically from distance into the middle distance of a screen or a dashboard. Small print often still needs reading glasses. Night-time haloes or glare are milder than with a multifocal for most people, though not absent.
03
Multifocal, including trifocal
A lens with rings that split incoming light between distance, intermediate and near, so that most tasks can be done without glasses. The trade-off is that the split reduces contrast a little, and rings or haloes around lights at night are noticed by some people, particularly early on. These designs depend on a healthy macula and a regular cornea, which is why the retina is examined before one is suggested.
MonofocalExtended depth of focusMultifocal
The explanation below describes this graphic. Drawing it requires JavaScript.
A general guide to what each design is intended to do, not a prediction for an individual eye. Glasses are often still helpful beyond the shaded range. Reading depends on the lens, the focusing target chosen, lighting and the health of the eye.
Which lens gives clear distance, intermediate and near vision?
Compare three ways a lens can focus light. Astigmatism correction is a separate feature, explained below.
Scroll sideways to compare all three lens designs.
Comparison of intraocular lens designs: what each brings into focus, whether astigmatism is corrected, and the typical trade-offs.
Compare by
The standard lensMonofocalOne point of focus, usually set for distance.
The standard lensExtended depth of focusA continuous range from distance into the middle distance.
The standard lensMultifocalIncluding trifocal. Light is split between distance, intermediate and near.
Typically in focus
NearIntermediateDistance
NearIntermediateDistance
NearIntermediateDistance
Astigmatism corrected?
Only in its toric version
Toric versions available
Toric versions available
Typical trade-offs
Glasses for reading and usually for computer work. The simplest optics, with the fewest night-time effects.
Reading glasses for small print for many people. Mild haloes or glare around lights at night for some.
Haloes and glare around lights at night for some people, and slightly less contrast in dim light. Depends on a healthy macula and cornea.
Typically in focusOften usable; glasses for fine detailUsually glasses
Near: reading. Intermediate: screens and dashboards. Distance: driving and television. Monofocal is the standard lens design.
How do I choose the right lens implant?
There is no best lens. There is a lens that suits this eye and this person, and the same design can be right for one and wrong for the other.
The health of the macula, the shape and surface of the cornea, previous laser vision correction and the other eye all narrow the sensible options before preferences come into it. Then the conversation turns to what you do most, how you feel about glasses for some tasks, and how you would take to haloes at night. Dr Chen will say plainly when a premium design is not the right choice for an eye.
Lens choice is the same conversation whether the operation is for a cataract or a refractive lens exchange, and the trade-offs are discussed before any lens is booked.
Dr Chen can offer any intraocular lens commercially available in Australia and is not tied to any single manufacturer.
That range runs from monofocal and toric lenses to extended depth of focus and multifocal designs. The freedom means the advice starts with your eyes, your measurements and the way you want to see, rather than with one company’s range.
For eyes that need something beyond a standard lens:
Custom high-power lenses. Some people with very high short-sightedness or long-sightedness need a lens power outside the range that standard lenses offer. Dr Chen uses custom-made lenses when an eye needs one.
Piggyback lenses. A second lens, such as the Sulcoflex or the 1stQ AddOn, can sit in front of an existing implant to correct a remaining focusing error or add a range of vision, without removing the first lens.
Lens power is calculated from several independent measurements with latest-generation formulas, and checked by an experienced team. That includes eyes after laser vision correction, radial keratotomy or keratoconus, eyes with very high myopia, and lens exchange.
Lens design and the intended focus are separate decisions. A monofocal lens, for example, can be chosen to favour distance or a nearer task.
DistanceIntermediate, about arm’s lengthNear, reading distance
Distance in both eyes
A common aim with monofocal lenses. Reading glasses are usually needed, and glasses may still improve other tasks.
Keeping a nearer focus
Some short-sighted people value reading without glasses. Tell Dr Chen before surgery; choosing distance focus changes that familiar pattern.
What is monovision?
Monovision or mini-monovision uses the two eyes together to extend the useful range. It needs a discussion about comfort, depth perception and your priorities.
Measurements help predict the required lens power, but healing and individual eye anatomy introduce uncertainty. A small residual prescription can remain even after careful planning.
Which lens designs suit my eyes, which do not, and why?
Will I need glasses for reading, computer work or driving with the lens you recommend?
Do I have astigmatism, and should it be corrected in the lens?
What are the trade-offs of the lens you recommend, particularly at night?
How does the health of my retina or cornea affect the choice?
What happens if I do not adapt to a multifocal or extended-depth lens?
Can the two eyes be set differently?
Common questions about lens implants
Is there a best lens?
No. Each design suits some eyes and some lives better than others. The recommendation follows your eye, particularly the retina and cornea, and what you want your vision to do.
Can I have a multifocal lens if I have macular degeneration or a membrane?
Often it is not the best choice: designs that split light between distances depend on a healthy macula. The trade-offs are explained candidly, and a monofocal or toric lens may be recommended instead.
Can a lens be changed later?
An intraocular lens can be exchanged in selected circumstances, although it is a more involved operation than the first. See the IOL exchange page.
Does the choice depend on the cornea?
Yes. Astigmatism, previous laser vision correction and the health of the corneal surface all affect which designs are sensible and how accurately the lens power can be predicted.
Vision Eye Institute confirms your appointment after you submit your request. The request form is not for emergencies. A referral is not strictly essential to request an appointment, but you need a valid one to claim a Medicare rebate for your consultation.