How is the eye measured?
Your eye is measured with the ZEISS IOLMaster 700 optical biometer and corneal mapping, and retinal imaging checks the macula. The lens power is calculated with latest-generation formulas and checked by an experienced team.
 Dr Simon ChenCataract & Retina Surgeon
Cataract surgery replaces the cloudy natural lens with a clear artificial lens chosen for your eye. It is day surgery, one eye at a time, usually taking under thirty minutes in theatre with anaesthetic drops or gel and sedation if wanted.
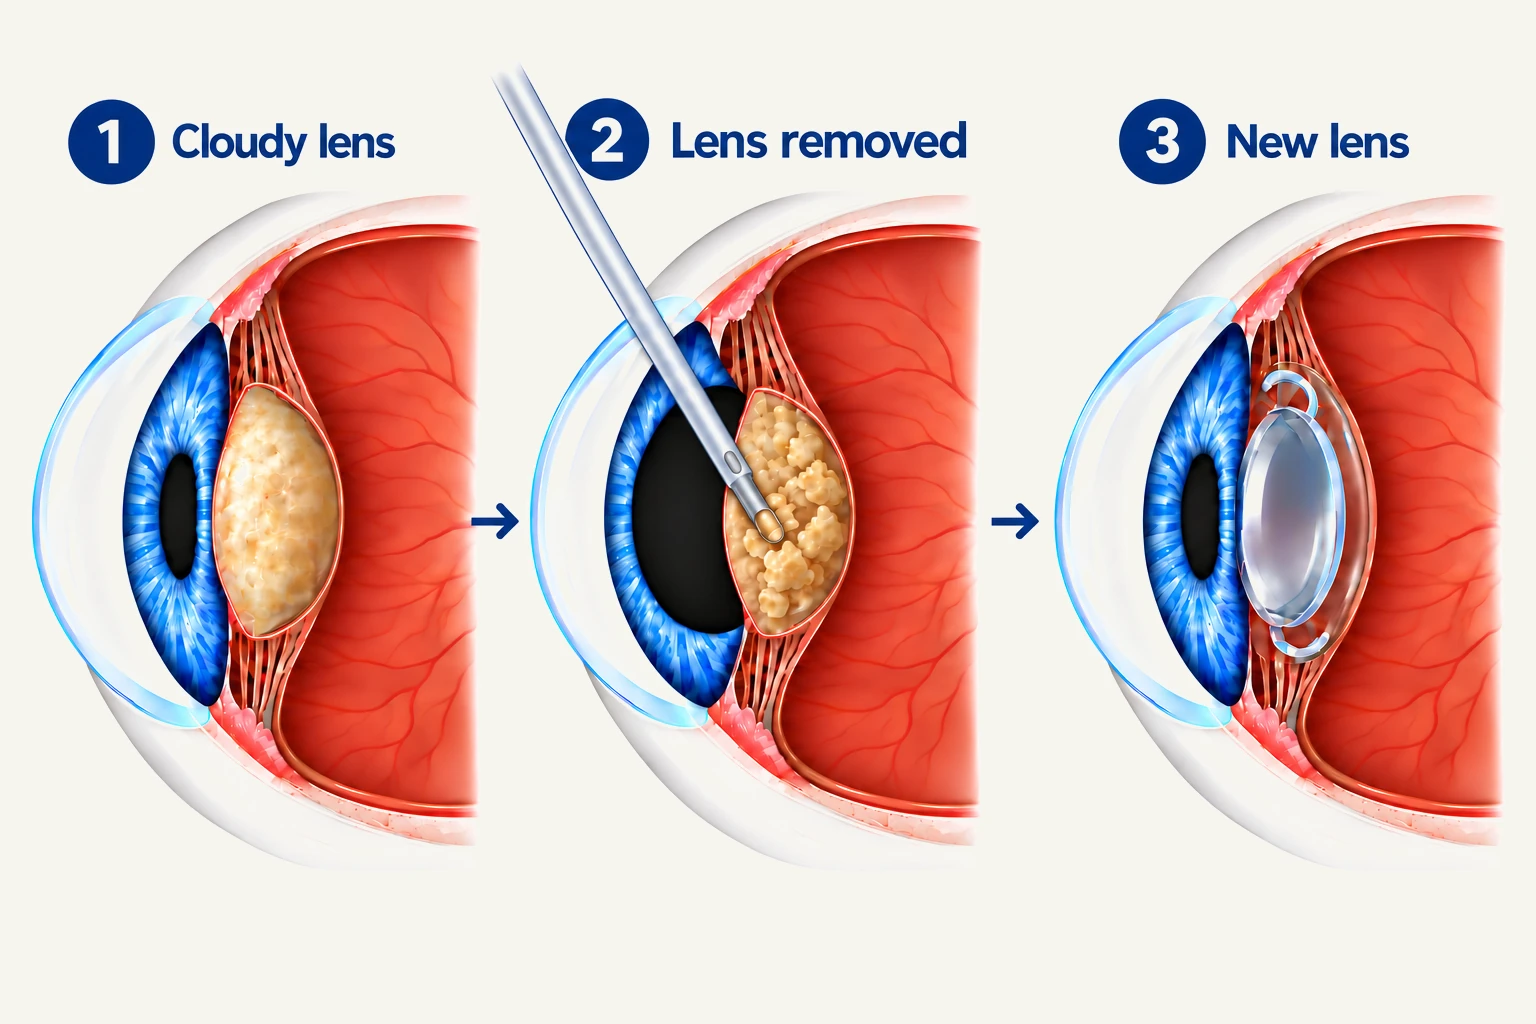
The main steps of cataract surgery. The cloudy lens material is removed and an artificial lens is placed inside the retained capsule.
Enlarge diagramThe cloudy lens is removed through a very small opening and replaced with a clear artificial lens that stays in the eye permanently.
The technique is called phacoemulsification. A fine probe uses ultrasound to break the cataract into tiny pieces, which are drawn out through the same opening. The new lens is folded, inserted and opened into the natural lens capsule. The incision is so small that it usually seals without stitches.
For the procedure, laser patterns and recovery, read our guide to YAG laser capsulotomy for capsule clouding.
If floaters appear after treatment for a cloudy capsule, read what to expect after YAG capsulotomy.
Cataract surgery is one of the most frequently performed operations in Australia. It is day surgery, one eye at a time, usually with a gap of a few weeks between eyes.
Your eye is measured with the ZEISS IOLMaster 700 optical biometer and corneal mapping, and retinal imaging checks the macula. The lens power is calculated with latest-generation formulas and checked by an experienced team.
Dry eye can cause fluctuating vision and unreliable measurements. Treatment and repeat measurements may be needed before the lens plan is finalised.
For practical instructions and illustrations, read the guide to lid hygiene for blepharitis. Follow your surgeon’s instructions about when to use this routine around surgery.
Tell us about contact lenses, previous LASIK or other laser vision correction, injuries and earlier eye surgery. Ask how long to leave contact lenses out before measurements; the interval depends on the lens type and your eye.
Discuss the activities you want to improve, the likely need for glasses and any limits imposed by the retina or cornea. Bring your medication list and follow your own instructions about medicines, fasting and transport.
How lens calculations are checked
Choosing the focus of your replacement lens →
Read When do I need cataract surgery? for help with the timing decision.
For one refractive full-range option, read about the RayOne Galaxy spiral lens. →
Dr Chen uses ZEISS CALLISTO eye digital guidance and the Alcon UNITY Vitreoretinal Cataract System (VCS) for cataract surgery in the day surgery upstairs from his clinic, with a femtosecond laser for selected patients.
Digital guidance. ZEISS CALLISTO eye recognises your eye and overlays your measurements in the operating microscope: where to make the incisions, the size and position of the capsule opening and, for a toric lens, the exact alignment. No ink marks are needed on the eye.
Cataract removal. The UNITY VCS is a state-of-the-art surgical system. It measures pressure and flow inside the eye continuously and adjusts in real time. It is designed to keep the eye stable and to protect the cornea throughout the operation.
Retinal back-up. Because the same system is used for retinal surgery, Dr Chen can usually manage an unexpected retinal problem during a cataract operation if one arises.
About the technology in Dr Chen’s practice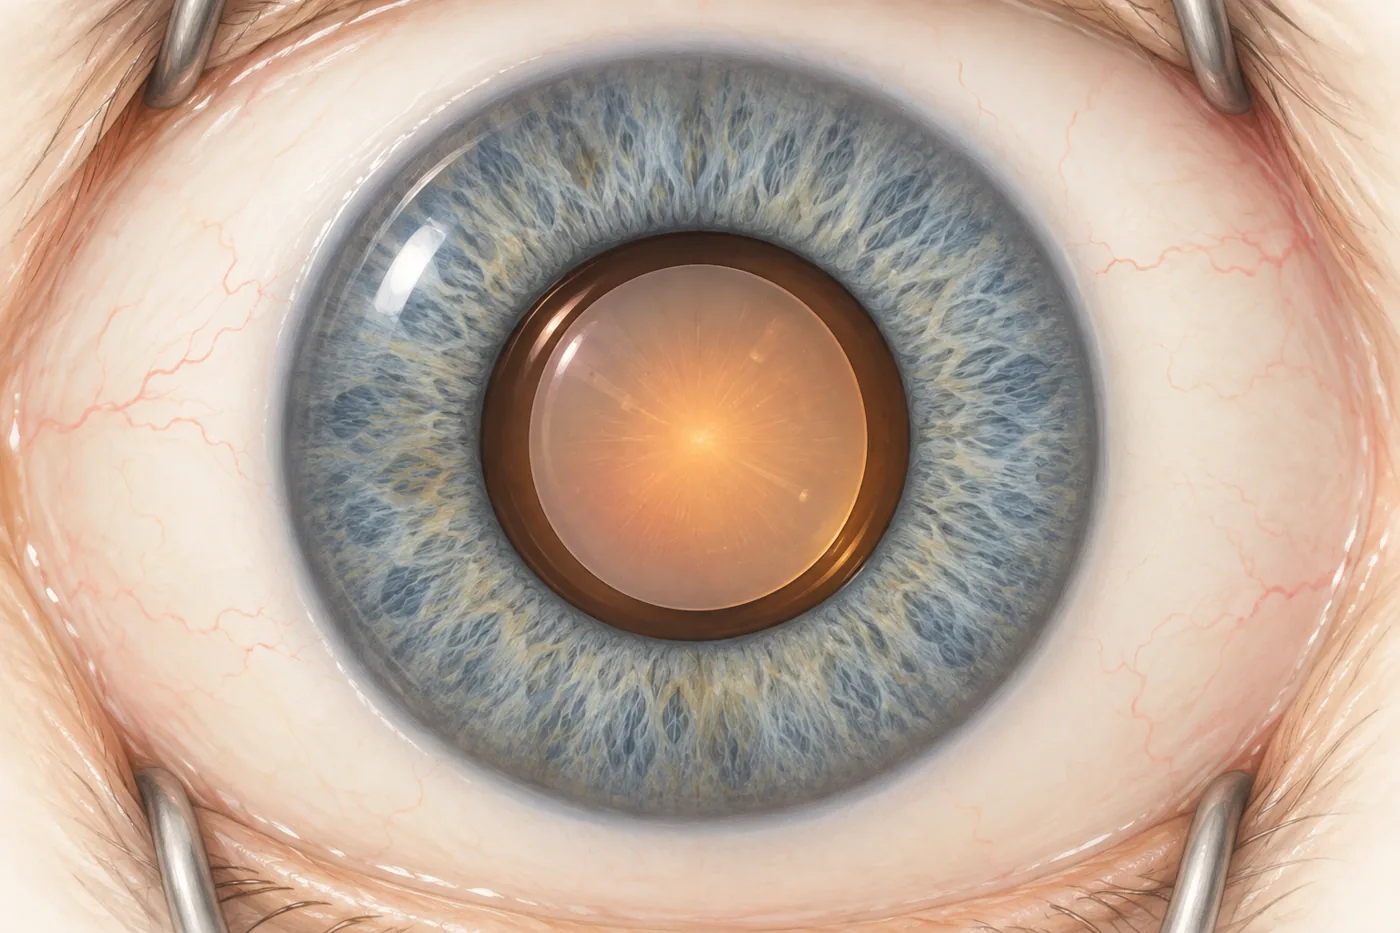
Drops are given to enlarge the pupil. The team confirms the eye, the lens and your details.
Usually anaesthetic drops or gel, often with light sedation so you are relaxed and comfortable. An injection around the eye is used when it suits the eye or the person better.
Through a tiny incision, ultrasound gently breaks up the cloudy lens so it can be removed. A folded artificial lens is placed in the same position and unfolds. Most operations take less than half an hour.
A short rest with a drink before you go home with a protective shield and drops. Someone needs to take you home.
Vision often improves within a day or two and settles over the following weeks. A review confirms the eye is healing as expected.
The day surgery is on level 4, directly above Dr Chen’s clinic on level 3, so your assessment, operation and follow-up visits all happen in the same familiar building.
Most people have cataract surgery awake, comfortable and unaware of the detail.
Anaesthetic drops or gel numb the surface of the eye. Many people also have light sedation from an anaesthetist, so the experience is calm rather than clinical. For some eyes, or for people who would rather not be aware of the operation at all, an injection around the eye or deeper sedation is the better choice.
The approach is decided with you beforehand, based on the eye, your general health and how you feel about the procedure. It is not one size fits all.

The central optic is the clear part of the lens. The curved arms, called haptics, help support it inside the eye.
Compare lens designs and optional features. Surface details and tint are enhanced for illustration; actual lenses vary.
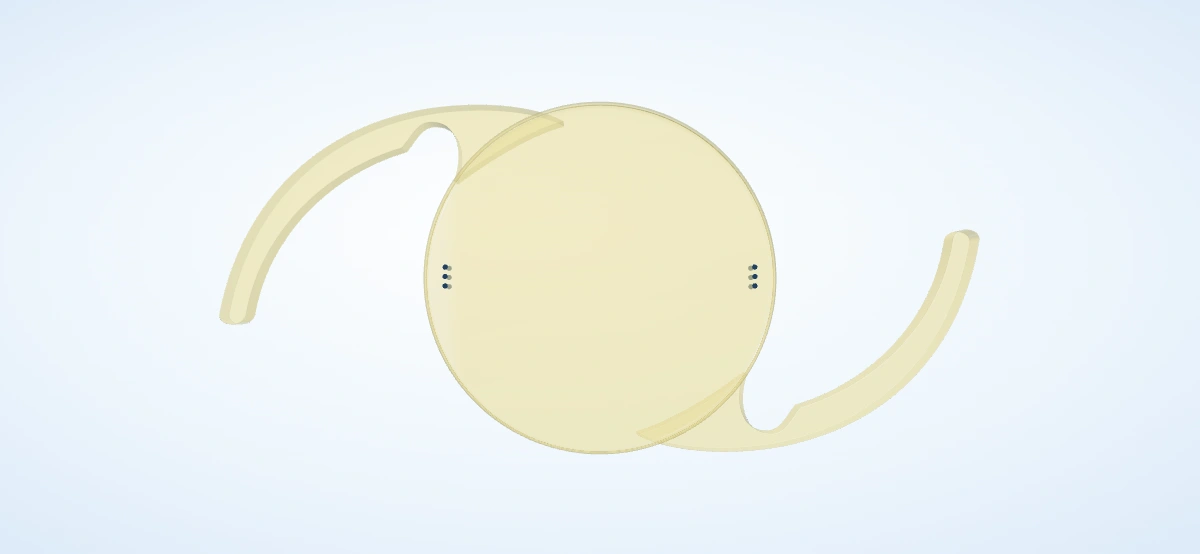
Sharp focus at one distance, usually far. Glasses for reading.
→Corrects astigmatism, and can be combined with other designs.
→Reduce dependence on glasses across distances, with trade-offs that suit some eyes and not others.
→There is no single best lens. The choice follows your eye, including the health of the retina, and what you want your vision to do day to day.
Explore the individual lens guides → · Astigmatism correction →
The explanation below describes this graphic. Drawing it requires JavaScript.
A general guide to what each design is intended to do, not a prediction for an individual eye. Glasses are often still helpful beyond the shaded range. Reading depends on the lens, the focusing target chosen, lighting and the health of the eye.
Many people have more than one thing going on. The plan should account for all of it.
Epiretinal membrane, macular hole, macular degeneration, previous vitrectomy or retinal surgery, high myopia, glaucoma and earlier laser vision correction all change the cataract conversation. They can affect the lens choice, the timing, the technique and what to expect afterwards.
Because Dr Chen operates on both the cataract and the retina, these situations are planned as one problem rather than handed between specialists. Where appropriate, a retinal procedure and cataract surgery can be considered together.
When a cataract and a retinal condition occur together, a retinal acuity meter can estimate how well the retina could see once the cataract is removed. This helps set realistic expectations before surgery.
IOL exchange and complex cataract
Most people are back to their usual activities within a few days, with drops for a few weeks.

Cataract surgery is a common operation and most people do very well. As with any operation, complications can occur, from minor irritation to rare sight-threatening problems. These are discussed with you before surgery, together with the reasons they are uncommon and how they are managed if they arise.
An uncommon complication is part of the cataract falling into the back of the eye during surgery. This is usually treated by a retinal surgeon. Dr Chen is also a retinal surgeon, and he has written guidance for other eye surgeons on managing it.
Read Dr Chen’s articleArrange someone to take you home and follow the hospital’s advice about having support afterwards. If drops are difficult, ask the team to demonstrate the technique and plan who can help. Keep your instructions and contact number easy to find.
Reading, television and screens can usually be resumed as comfort allows. Vision may fluctuate while the eye settles. Use prescribed drops, avoid rubbing the eye, and follow your instructions about the shield, washing and activity restrictions.
Office work and a dusty or physical job have different demands. Ask for advice specific to your work, swimming, sport and travel plans. Driving requires adequate vision and the advice of your treating team, rather than a fixed number of days.
The early checks assess healing and eye pressure; later review considers the final focus and any glasses needed. Seek urgent advice for increasing pain or redness, worsening vision, new flashes or a sudden increase in floaters.

The most common reason is posterior capsule opacification (PCO), sometimes called a “secondary cataract”. The cataract has not grown back, and PCO is usually easily treated with a quick laser procedure in the clinic.
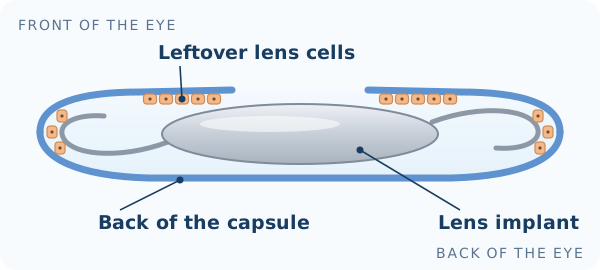
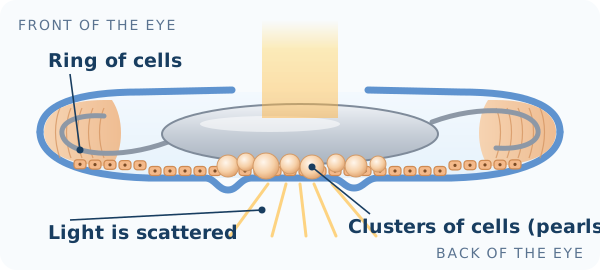
During cataract surgery the cloudy lens is removed, but the thin, clear capsule that held it is left in place to support the lens implant. A small number of the eye’s own lens cells always remain on the inside of this capsule, because they cannot all be removed.
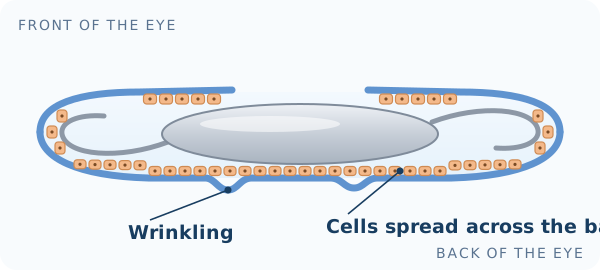
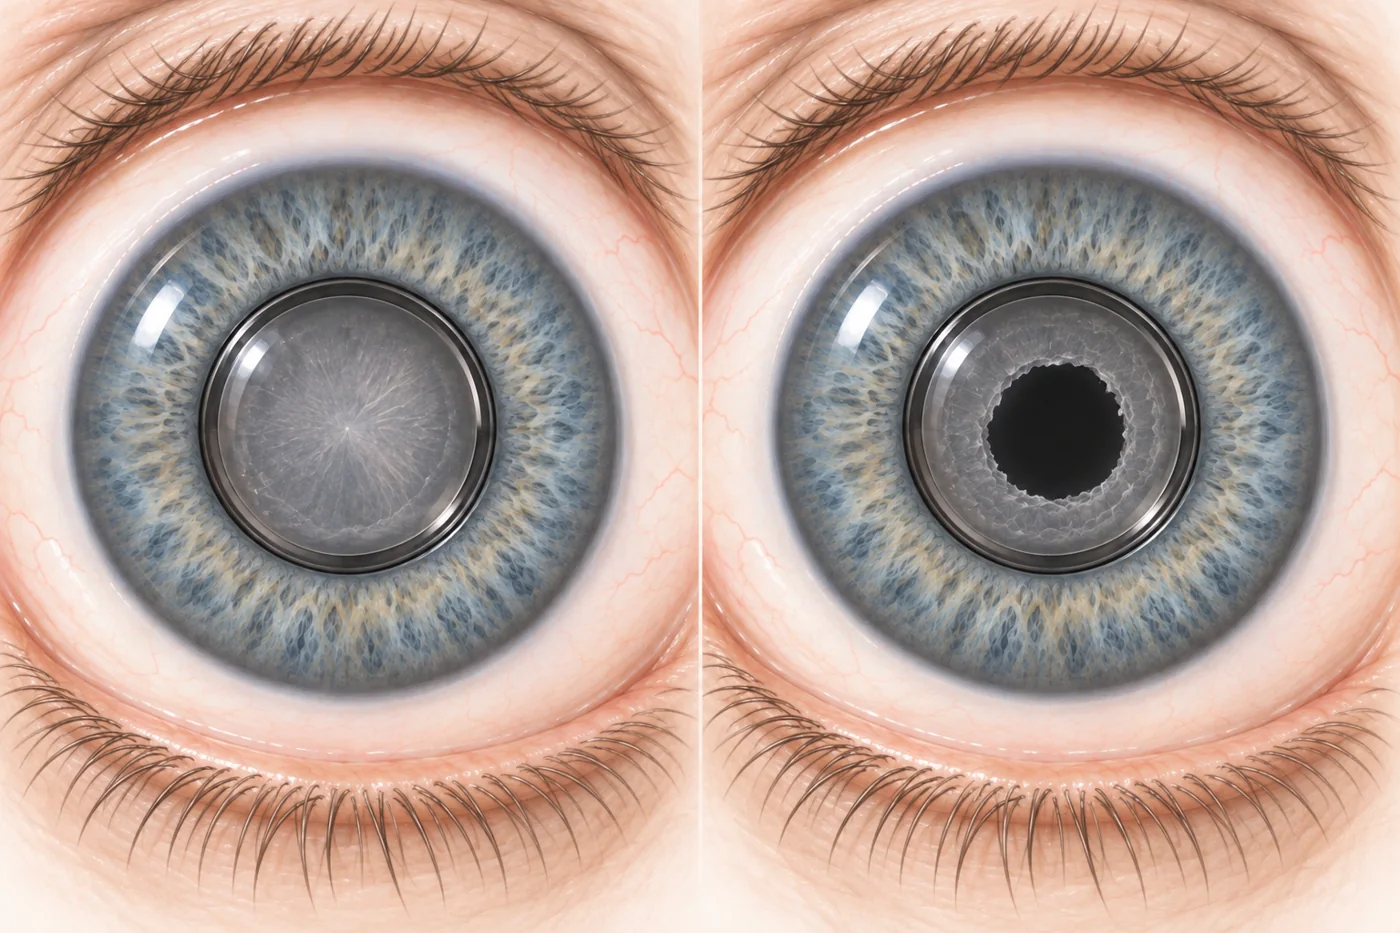
Over months or years, some of these cells can grow and spread across the back surface of the capsule, behind the implant. They form a thin hazy layer, sometimes with fine wrinkles or small clusters of cells, which scatters light and blurs vision.
PCO is one of the most common reasons for vision to become blurred again after cataract surgery. Modern lens implant designs and surgical techniques have reduced how often it happens, but some people still develop it, occasionally many years later. It tends to be more common in younger people and in eyes with inflammation.
Typical symptoms are gradually increasing blur, glare from lights or haze, rather like the original cataract.
PCO can cause gradual blur or glare. An examination checks whether it explains your symptoms, because the retina, eye surface or glasses prescription can also affect vision.
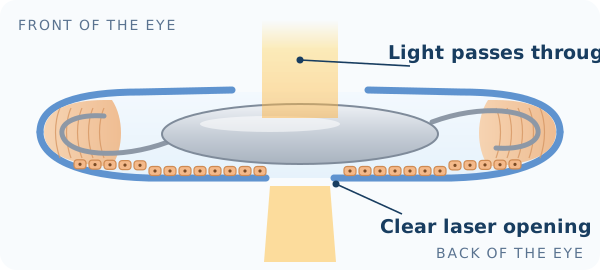
When PCO affects vision, a laser can create a small opening in the cloudy capsule. Treatment is usually performed in the clinic after drops. Temporary floaters or inflammation can occur; raised eye pressure, retinal swelling or retinal detachment are possible complications.
Arrange transport if dilating drops are used and follow the advice given about driving and review.
The eye is numbed and most people feel pressure or light touch rather than pain. Some grittiness for a day or two afterwards is normal.
Usually not fully. Most people have anaesthetic drops with light sedation and remember little. Sedation helps you feel comfortable and relaxed throughout the procedure. Deeper sedation is available when it suits the person or the eye.
Usually one eye at a time, a few weeks apart, so the first eye can settle and the plan for the second can be refined.
Many people return to desk work within a few days. Driving depends on your vision meeting the standard, usually confirmed at the first review.
No. Some people later develop haze on the capsule behind the new lens, which is cleared with a short laser treatment in the clinic.
It can be. Vitrectomy often speeds up cataract development, and cataract surgery afterwards can be more technically demanding. Dr Chen regularly performs cataract surgery in eyes that have had vitrectomy, and plans it with the retinal history in mind.
Longer articles by Dr Chen go into these questions in more detail, including what the research shows.
For the evidence and practical options, read Can cataracts be treated without surgery?
Cataract surgery after radial keratotomy (RK) explains why repeat measurements, specialised lens calculations and careful wound placement matter, and why a refractive surprise can still occur.
Public or private cataract surgery compares waiting times, surgeon choice, supervised training, lens availability and costs in Australia.
Appointments and enquiries are made through Vision Eye Institute Chatswood.
Level 3, 270 Victoria Avenue, Chatswood NSW 2067Optometrists, GPs and ophthalmologists can refer through Oculo or with the PDF referral form.
Vision Eye Institute confirms your appointment after you submit your request. The request form is not for emergencies. A referral is not strictly essential to request an appointment, but you need a valid one to claim a Medicare rebate for your consultation.